
Overview
Acute Lymphocytic Leukemia (ALL) in adults is an aggressive malignancy of the bone marrow where immature lymphoid cells proliferate and crowd out normal blood production.
Prompt diagnosis, risk stratification, and multi-agent therapy are essential because adult ALL behaves more aggressively than childhood ALL and requires tailored treatment plans involving chemotherapy, targeted agents, and sometimes stem cell transplant.
Supportive care (infection prevention, transfusions) and close monitoring of complications are equally important.
Overview And Clinical Background
Biology, incidence, and clinical importance
ALL arises from malignant transformation of lymphoid precursor cells in the marrow or blood.
In adults the disease often presents with higher-risk features and different genetic drivers than pediatric ALL, so management is individualized based on cytogenetics and molecular markers.
- Pathogenesis: Clonal expansion of immature B- or T-lymphoid blasts that impair normal hematopoiesis.
- Epidemiology: Less common in adults than children but carries higher risk and different biology.
- Prognostic markers: Cytogenetics (e.g., Ph chromosome), molecular mutations, and response to therapy guide prognosis.
Symptoms, Signs And Presentation
Presentation is typically subacute with symptoms of marrow failure and organ infiltration.
Early recognition of these signs speeds diagnosis and treatment initiation.
- Cytopenia-related: Fatigue, pallor from anemia; easy bruising or bleeding from low platelets.
- Infections: Frequent or severe infections due to neutropenia or dysfunctional lymphocytes.
- Mass effects: Lymphadenopathy, splenomegaly, or mediastinal mass (especially with T-cell ALL).
Diagnosis Methods And Investigations
Blood, marrow and molecular testing
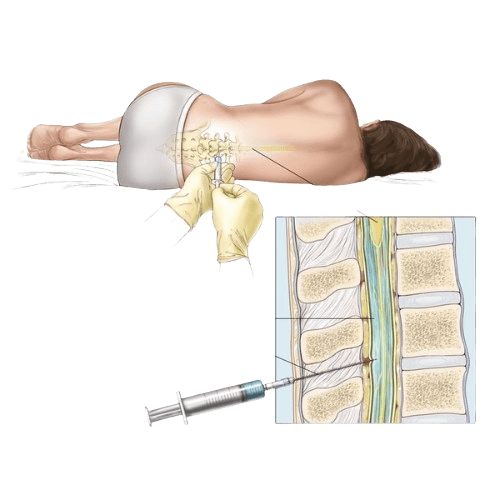
Diagnosis requires blood counts, peripheral smear, and bone marrow examination with immunophenotyping.
Molecular and cytogenetic tests refine risk and treatment strategy.
- Peripheral blood and marrow: Blast percentage on smear and hypercellular marrow with lymphoblast infiltration.
- Immunophenotyping: Flow cytometry to classify B- versus T-lineage and therapeutic targets.
- Genetic testing: Cytogenetics, FISH, and PCR for Ph chromosome, BCR-ABL, and other actionable mutations.
Treatment Options And Surgical Techniques
Treatment is multi-phase and often intensive—induction, consolidation, maintenance—and may include targeted agents or transplant.
Supportive measures and infection control are integrated components.
- Induction chemotherapy: Multi-agent regimens to achieve remission (e.g., anthracycline, vincristine, steroids ± targeted drugs).
- Consolidation and maintenance: High-dose cycles to eradicate residual disease; maintenance therapy reduces relapse risk.
- Allogeneic stem cell transplant: Considered for high-risk or relapsed patients to achieve long-term remission.
Recovery, Risks And Prognosis
Early complete remission predicts better outcomes, but adults have higher relapse risk than children.
Complications include infection, bleeding, organ toxicity from chemo, and transplant-related effects; multidisciplinary care improves survival and quality of life.
Why Choose Us
CureU Healthcare offers coordinated hematology-oncology care with modern diagnostic panels, access to targeted therapies and transplant programs, and comprehensive supportive care.
We personalize treatment plans and focus on toxicity management and survivorship.
Conclusion
Adult ALL is treatable and often curable with prompt, risk-adapted therapy and specialist support.
Early referral and adherence to protocolized care at an experienced center improve odds for lasting remission.

B.U.M.S, M.D. (NAT) | Reg No. 9153 | Ex. Secretary & Treasurer, N.I.M.A.
Qualified healthcare professional in Unani and Naturopathic medicine with deep expertise in traditional healthcare systems, patient-centered clinical care, and medical content review.











